TMS Therapy
Outpatient magnetic pulses targeted at mood circuits. Done while fully awake with zero post-session downtime or memory-loss risks, performed 5 days a week for 4 to 6 weeks.

PHONE: 252-364-8972
TRUE NORTH IMH
102 OAKMONT DR., SUITE 30
GREENVILLE, NC 27858
BY APPOINTMENT ONLY
TUES-FRI. 8:30AM-6PM
SAT-SUN. CLOSED
When depression persists despite therapy and medication, brain stimulation options like TMS and ECT offer effective paths forward—differing significantly in treatment intensity, side effects, and daily recovery needs.
Outpatient magnetic pulses targeted at mood circuits. Done while fully awake with zero post-session downtime or memory-loss risks, performed 5 days a week for 4 to 6 weeks.
Controlled electrical stimulus inducing a therapeutic seizure under general anesthesia. Typically used for urgent, severe cases, catatonia, or immediate suicide risk.
Neither option is universally "better." Selection depends on symptom severity, response urgency, prior treatment history, medical eligibility, and tolerance for potential memory risks.
When depression does not improve enough with medication or psychotherapy, brain stimulation treatments may become part of the conversation. Two of the best-known options are transcranial magnetic stimulation (TMS) and electroconvulsive therapy (ECT). Both can treat depression, but the experience, treatment intensity, side effects, and situations in which they are used are different.
The most important point is that TMS and ECT are not interchangeable treatments, and one is not automatically the better choice for every person. TMS is an outpatient treatment that uses magnetic pulses while you remain awake. ECT is also noninvasive, but it is performed under general anesthesia and intentionally produces a brief, controlled seizure. The right treatment depends on depression severity, urgency, medical history, prior treatment response, side-effect concerns, and personal preferences.
| Comparison | TMS | ECT |
|---|---|---|
| How it works | Magnetic pulses stimulate targeted brain circuits involved in mood. | A controlled electrical stimulus produces a brief therapeutic seizure. |
| Anesthesia | No general anesthesia. | General anesthesia and a muscle relaxant are used. |
| Awake during treatment | Yes. | No. |
| Typical setting | Outpatient clinic. | Hospital or specialized clinical setting; may be inpatient or outpatient. |
| Typical course | Often 5 days a week for about 4 to 6 weeks, depending on protocol. | Often 2 to 3 treatments a week, commonly totaling about 6 to 12 treatments. |
| After treatment | Most people can return to normal activities, including driving, after a session. | Recovery and driving restrictions are required because of anesthesia and possible confusion or memory effects. |
| Common side effects | Headache, scalp discomfort, tingling, facial twitching, or lightheadedness. | Confusion, memory problems, headache, nausea, jaw pain, or muscle aches. |
| Often considered when | Depression has not improved enough with standard treatment and a lower-burden outpatient option is appropriate. | Depression is severe or treatment-resistant, or a rapid response is needed, including some cases involving suicidality, psychosis, catatonia, or failure to eat or drink. |
Transcranial magnetic stimulation uses an electromagnetic coil placed against the scalp to deliver repeated magnetic pulses to brain regions involved in mood regulation. For major depressive disorder, treatment commonly targets the prefrontal cortex. TMS does not require surgery, anesthesia, or an induced seizure.
During a session, you remain awake and may feel tapping on the scalp and hear clicking from the device. Session length varies by the TMS protocol. According to Mayo Clinic's overview of TMS, commonly used protocols can range from only a few minutes to about 20 minutes, and a treatment course often involves sessions five days a week for four to six weeks.
TMS is most commonly used for major depression that has not improved sufficiently with standard treatments. True North IMH also provides a dedicated
TMS treatment for depression program in Greenville, North Carolina.
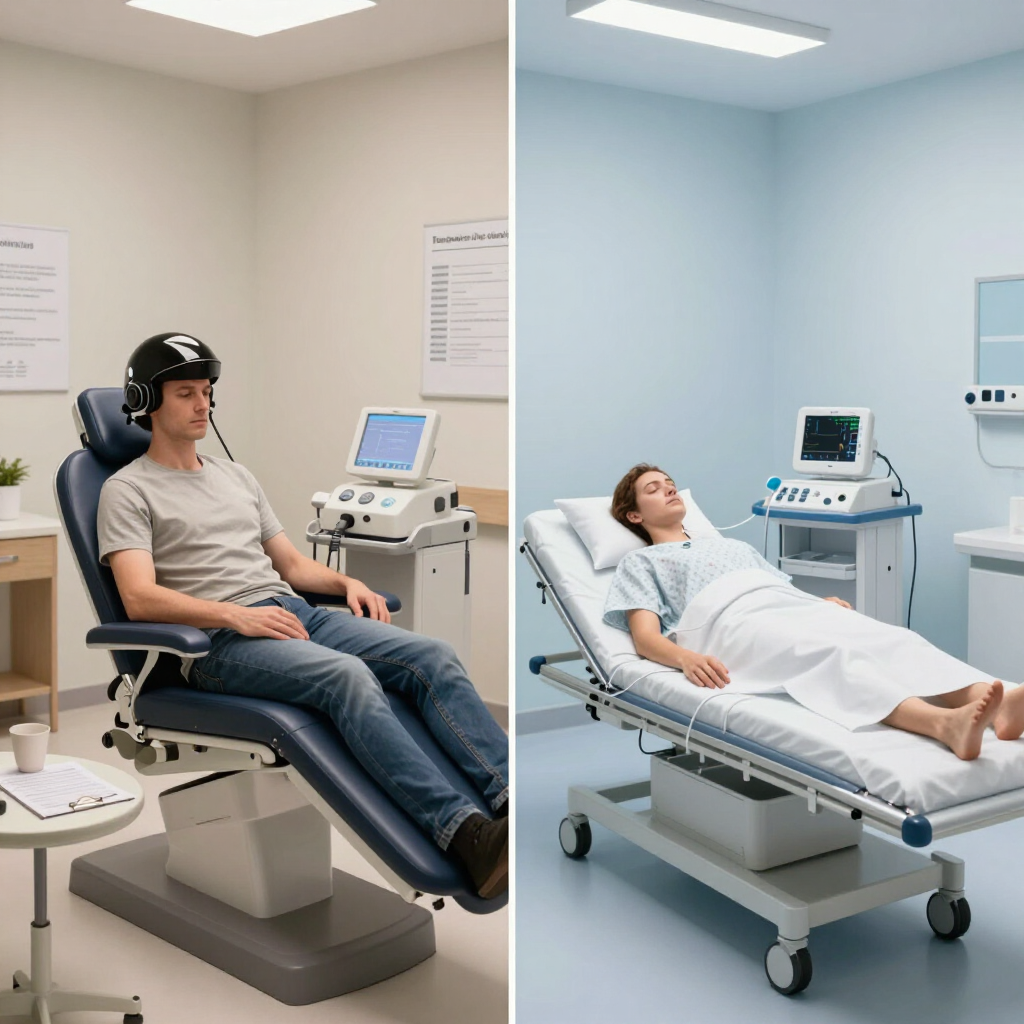
TMS and ECT differ substantially in what happens before, during, and after treatment.
You remain awake and seated during treatment.
A coil delivers repeated magnetic pulses to targeted brain regions.
Most people can resume normal activities after the session.
Treatment takes place with general anesthesia and medical monitoring.
A controlled electrical stimulus produces a brief therapeutic seizure.
Temporary confusion or memory effects can occur, and driving restrictions apply.
Electroconvulsive therapy uses a carefully controlled electrical current to trigger a brief seizure while the patient is under general anesthesia. Modern ECT is very different from the historical images that still shape public perception. Treatment includes anesthesia, a muscle relaxant, oxygen, and monitoring of brain activity, heart rhythm, blood pressure, and oxygen levels.
The
National Institute of Mental Health notes that ECT is often considered for severe treatment-resistant depression or when a rapid response is needed because the situation is life-threatening, such as severe suicidality, catatonia, or malnutrition. A typical acute course is commonly completed over several weeks.
Both treatments can reduce depressive symptoms, including in people who have not improved with medication. Their effectiveness is difficult to compare with one simple percentage because studies use different patient populations, TMS protocols, ECT techniques, definitions of treatment resistance, and outcome measures.
ECT has a long history of use and remains an important treatment for severe and urgent depression. TMS also has strong evidence for treatment-resistant depression and offers a substantially different treatment experience. A
2025 systematic review and network meta-analysis found no statistically significant differences in response or remission among ECT, repetitive TMS, and intravenous ketamine in the included trials, but the authors rated confidence in that comparative evidence as very low. That uncertainty is one reason treatment selection should be individualized rather than based on a single headline response rate.
TMS is generally well tolerated. Common effects include scalp discomfort, headache, tingling, facial muscle twitching, and lightheadedness. These effects are usually temporary and often become easier to tolerate as treatment continues. Serious complications such as a seizure are rare, which is why screening for seizure risk, implanted devices, and other medical factors is part of a proper TMS evaluation.
ECT has a different risk profile because it involves anesthesia and a therapeutic seizure. Common effects include temporary confusion, headache, nausea, jaw or muscle aches, and memory problems. Mayo Clinic's ECT guidance notes that many memory problems improve after treatment, although some people can have more persistent gaps in memory, particularly for events around the treatment period.
Concerns about cognition are therefore a meaningful part of the TMS vs. ECT discussion. TMS does not typically cause the memory loss associated with ECT, while ECT may still be appropriate when the expected benefit of a faster, intensive treatment outweighs that risk.
TMS is designed to fit into an outpatient routine. Most patients can drive themselves to and from treatment and return to work, school, or normal activities after a session.
ECT requires more planning. Because anesthesia is used and temporary confusion can occur, patients need transportation and must follow their treatment team's instructions about driving, work, and important decisions. Some people receive ECT as an outpatient, while others receive it during a hospital stay because of the severity of their illness.

A clinician may discuss TMS when depression continues despite appropriate trials of medication or psychotherapy, especially when a person wants a nonmedication treatment that does not require anesthesia and can be completed in an outpatient setting.
ECT may enter the discussion when depression is especially severe, when psychotic symptoms or catatonia are present, when a person is not eating or drinking adequately, when suicide risk creates a need for rapid treatment, or when ECT has worked well in the past.
If you are still trying to understand why standard treatment has not helped, True North IMH's guide on what to do when antidepressants do not work explains how clinicians may reassess diagnosis, medication response, side effects, and other treatment options before moving forward.
True North Integrative Mental Health provides outpatient TMS therapy and psychiatric care for patients in Greenville, Pitt County, and surrounding Eastern North Carolina communities. TMS may be worth discussing if depression has not improved enough with medication or therapy and you are looking for an option that does not require anesthesia or expected downtime after each session.
If symptoms are severe, rapidly worsening, psychotic, catatonic, or associated with immediate suicide risk, urgent psychiatric or emergency evaluation is more appropriate than waiting for a routine TMS consultation.
To discuss whether TMS could fit your treatment history and goals, contact True North IMH to request a consultation in Greenville, NC.
Unsure whether TMS or ECT is the right next step for your depression treatment? Request a consultation with True North IMH or call 252-364-8972 to discuss your treatment history, insurance coverage, and personalized options.
No. TMS uses magnetic pulses and does not intentionally cause a seizure or require anesthesia. ECT uses an electrical stimulus under general anesthesia to produce a brief therapeutic seizure.
Memory loss is not an expected common side effect of TMS. ECT can cause temporary confusion and memory problems, and some people may experience more persistent memory gaps.
Yes. Modern ECT remains an established treatment, particularly for severe or treatment-resistant depression and situations in which a rapid clinical response may be necessary.
Not in every situation. TMS and ECT have different clinical roles. TMS may be appropriate for many people with treatment-resistant depression, while ECT may be considered when symptoms are especially severe or urgent.
ECT is often selected when speed is a major clinical priority. TMS improvement commonly develops across a multiweek treatment course. The timing of response varies from person to person with either treatment.
Get help with depression today! It's important to know that you are not alone.
At True North IMH in Greenville, NC, our neurocare and psychiatric services are dedicated to enhancing mental well-being within the local community and across Pitt County. We excel in delivering tailor-made treatment plans designed to assist you in achieving a more fulfilling life.
Our dedicated team is unwavering in their commitment to assist you on your individual path toward improved mental health, whether you are contending with anxiety, depression, PTSD, ADD, or any other mental health challenge.
Located in the heart of Greenville North Carolina? We're here to provide support!
or call/text: (252) 364-8972
TRUE NORTH IMH
102 OAKMONT DR., SUITE 30
GREENVILLE, NC 27858
NAVIGATION